


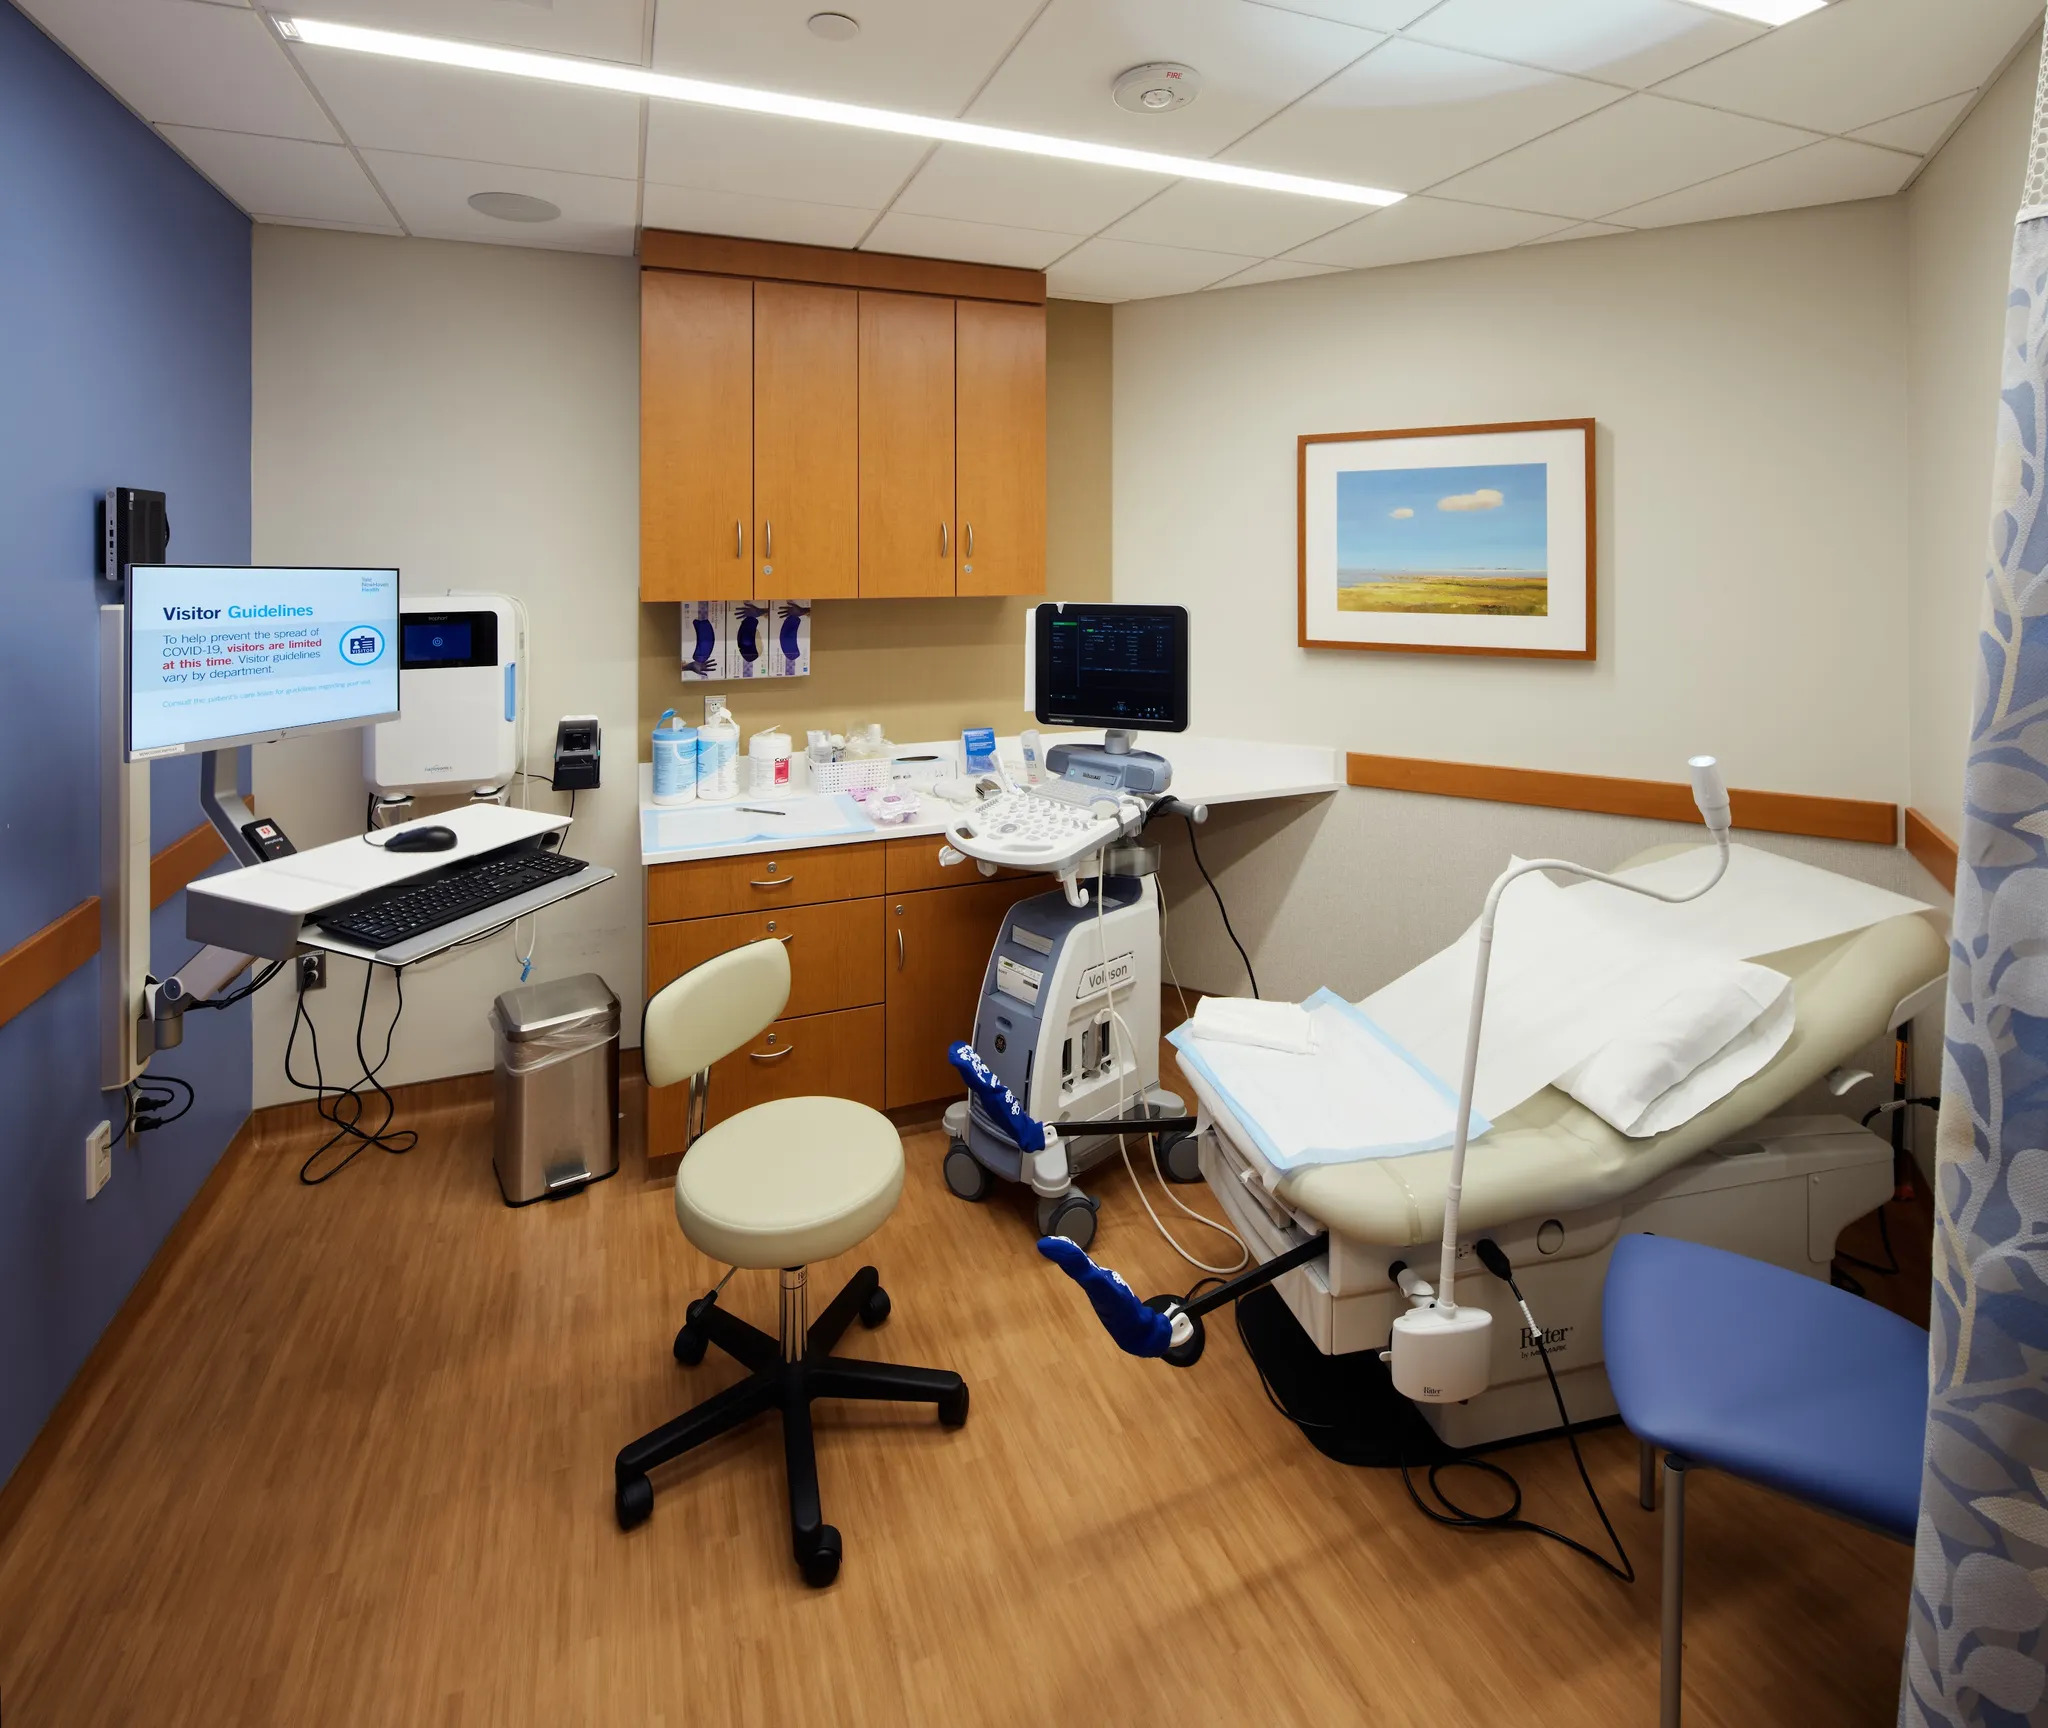
About Yale Medicine Fertility Center
Yale Medicine Fertility Center is Yale School of Medicine’s assisted reproduction program, and it works like one. Care is delivered at five Connecticut campuses — Orange, where the listed practice address for the program’s physicians is 200 West Campus Drive, plus New Haven, Westport, Guilford and Stamford — while the same physicians hold faculty appointments in Yale’s Department of Obstetrics, Gynecology and Reproductive Sciences. Yale trains reproductive endocrinology fellows in this department, so a trainee may be present at your visit. The practical upside of the university structure shows up when a cycle stops being routine: reproductive surgery, oncology, genetics, high-risk obstetrics and anesthesia are inside one institution rather than a phone call away.
The outcomes, and what the rows actually measure. SART publishes this program under its registry name, Yale Fertility Center (clinic ID 2187). In the 2023 final report, the program ran 814 cycles against a national per-clinic average of 738. Live birth per egg retrieval, counting all embryo transfers, came in at 57.9% for women under 35 (95 cycles), 37.6% at 35-37 (101 cycles), 23.3% at 38-40 (73 cycles), 13.2% at 41-42 (38 cycles) and 0% over 42 (56 cycles). Compared with the national rows carried in the table on this page, Yale is above the country under 38, below it at 38-40 (23.3% against 25.1%), and well below it for patients over 40 (5.3% against 10.8%). The over-40 cell on the comparison table blends SART’s two published bands; the split figures are in the sentence above, and both rest on few cycles.
The higher set of numbers on this page — 72.2% under 35, 54.8% at 35-37, 30.6% at 38-40 — is SART’s new-patient measure, which counts patients rather than cycles (72, 62 and 36 new patients respectively) and credits every transfer one patient completes. It always reads higher than a per-retrieval rate at the same clinic, so never compare one clinic’s new-patient figure with another’s per-retrieval figure. Whichever row you use, the shape of the story is the same: strong under 38, average at 38-40, and behind the national number once you are past 40.
Volume and results both moved around across the reported years: 690 cycles in 2020, 920 in 2021, 995 in 2022, 814 in 2023, and 865 in the 2024 preliminary year. That 2024 report is the one to read carefully, because its under-35 live birth per retrieval dropped to 44.0% (109 cycles) from 57.9% the year before, and the new-patient under-35 figure dropped to 51.9% (79 patients) from 72.2%. A preliminary SART year is incomplete and gets revised; it is also one year at one clinic, and single-year swings of this size happen on small denominators. Do not rank clinics on a preliminary column.
The academic profile belongs to the department and to individual physicians rather than to the clinic as a ranked unit. Yale’s obstetrics, gynecology and reproductive sciences department receives more than $5 million a year in NIH funding; its chair, Hugh Taylor, was elected to the National Academy of Medicine in 2016 and served as president of the American Society for Reproductive Medicine in 2020-2021; David Seifer, who directs the program’s REI training, served as president of the Society for Assisted Reproductive Technology in 2017-2018. Those are real credentials. No body publishes a comparative ranking of this clinic against Connecticut’s other programs, so treat the name as a statement about who works there and about how the data gets reported, not about where it ranks.
Accreditations & Awards
- SART membership with annual CDC reporting. Every cycle is reported to the Society for Assisted Reproductive Technology and onward to the CDC under the federal reporting requirement that has applied to U.S. fertility centers since 1992. Five reporting years are public for this clinic, 2020 through 2024, which means you can pull the age-band tables yourself instead of relying on a coordinator’s summary.
- CLIA-certified laboratory work. The program states CLIA coverage for its laboratory testing. No certificate number appears in its public material, so ask for it if you want to verify the certificate yourself.
- LifeAire air handling in the embryology lab. The program’s laboratory is fitted with a LifeAire system that it describes as removing 99.99% of biological and chemical contaminants from the air supplied to embryo culture. The embryology team is led by doctoral-level embryologists.
- Computer-assisted semen analysis (CASA). Semen evaluation is instrumented rather than eyeballed, and the male fertility program lists a reproductive urologist, which puts surgical sperm retrieval and varicocele work inside the same practice.
- Department-level research funding. More than $5 million per year in NIH support to Yale’s obstetrics and gynecology department, sustained for over 20 years for its chair. This funds the laboratories, not your cycle.
- Named national roles. Hugh Taylor, National Academy of Medicine member (2016) and ASRM past president (2020-2021). David Seifer, SART past president (2017-2018), and the recipient of a 2011 Thomas Alva Edison Patent Award tied to the anti-Müllerian hormone ovarian reserve test his work supported. Emre Seli, who directs the IVF program, has published an AI embryo-selection model, FORTUNE, developed with his group.
- What is not documented. No CAP or joint-commission laboratory accreditation appears in the program’s own material; there is no published price list, no elective single-embryo-transfer rate, no multiple-birth rate, no published wait from first call to cycle start, and no breakdown of outcomes by campus — SART posts one clinic record for all five. Aggregate patient reviews for the listing average 3.4 out of 5 across 153 ratings, and that instrument mostly records scheduling and front-desk experience rather than clinical results.
Why Choose Yale Medicine Fertility Center
Five campuses, one physician group. You can be seen in Orange, New Haven, Westport, Guilford or Stamford while your records, laboratory and cycle team stay in one system. A stimulated cycle asks for monitoring every other day and often at dawn, so the campus you can reach changes what treatment costs you in time off work. The Orange campus has free patient parking.
Preservation options that require a surgical program. Alongside egg, embryo and sperm freezing, the center offers ovarian tissue freezing for patients who cannot wait the couple of weeks a stimulation cycle takes, and testicular tissue freezing. Ovarian tissue cryopreservation is the option that matters when chemotherapy starts on a fixed date. The program runs its preservation work with Yale’s oncology service.
Subspecialty clinics with named directors. PCOS and menopause care are each run as a formal program under Lubna Pal. A multidisciplinary recurrent pregnancy loss service brings reproductive endocrinology, maternal-fetal medicine, reproductive immunology and genetics to one evaluation. LGBTQ+ family building — IUI and IVF with donor sperm or donor eggs, gestational carrier cycles, and fertility preservation for transgender patients — is listed as a service line for same-sex couples and single patients rather than handled case by case.
An embryology lab with a published air-quality specification. Time-lapse culture, in-house PGT biopsy capability and default blastocyst-transfer policy are not settled by the program’s public materials, and you should ask about all three. What is documented is the air-handling system and a doctoral-level embryology team.
Research access that only academic sites carry. The program lists interventional studies for patients, including a trial of pre-IVF GnRH antagonist treatment in women with endometriosis. If a study exists that you would qualify for, ask the coordinator which tests, medications and procedures the sponsor covers and which you pay for.
Depth behind the clinic. Yale New Haven Hospital is the same institution: endometriosis excision and uterine surgery, reproductive urology, genetics counseling and high-risk obstetrics are reachable without changing providers.
IVF & Fertility Services
- In Vitro Fertilization (IVF) with individualized stimulation protocols, transvaginal retrieval under sedation, embryo culture to day 5 or 6, and fresh or frozen transfer.
- ICSI (Intracytoplasmic Sperm Injection) for severe male factor and for prior fertilization failure.
- IUI (Intrauterine Insemination) with partner or bank donor sperm, for mild male factor, unexplained infertility, single patients and same-sex couples.
- PGT-A and PGT-M. Preimplantation testing for chromosome number and for known single-gene conditions, on informed consent.
- Egg, embryo and sperm freezing, both elective and before gonadotoxic treatment.
- Ovarian and testicular tissue freezing for patients with no time for a stimulation cycle.
- Donor egg, donor sperm and donor embryo programs, with genetic-history screening and matching through the program’s donor services.
- Gestational carrier cycles for patients without a uterus, with uterine pathology, or for male couples; the program requires carriers to be found through an agency.
- Male infertility evaluation and treatment through the male fertility program, including reproductive urology consultation, computer-assisted semen analysis, and surgical sperm retrieval.
- Recurrent pregnancy loss evaluation by a multidisciplinary team, covering hormonal, anatomic, genetic and immunologic causes.
- Endometriosis and fibroid care, including the medical and surgical management that precedes a stimulation cycle.
- PCOS management and menopause care as named programs.
- Fertility preservation counseling for transgender patients.
- Third-party reproduction counseling covering the medical, legal and emotional sides of donation and surrogacy.
Fees & Packages
There is no published price list. The program posts no cycle fee, no medication estimate, no donor egg or gestational carrier package price, and no financing plan, so treat any figure you are given verbally as a quote to be compared against a second center.
Money questions go to the center’s financial counselors, who check your benefits before treatment starts and are the right people to ask what your plan actually covers in Connecticut. The program states that it works with a range of insurance plans.
One coverage rule is on your side and is worth citing when you are turned down. Connecticut requires health plans to cover fertility preservation for cancer patients aged 40 and under, which means preservation before chemotherapy or pelvic radiation is an insurance question in this state rather than a cash question. Self-funded employer plans are governed by federal law rather than a state mandate, so if you are refused, ask in writing whether your plan is self-funded and get the denial on paper.
When you request a written estimate, ask it to itemize the pieces clinics separate out: monitoring scans and bloodwork, anesthesia at retrieval, the insemination or ICSI charge, embryo culture and freezing, PGT biopsy and laboratory fees per embryo, annual storage for eggs, embryos or tissue, and any surgical step such as a hysteroscopy done in the same cycle. Ask which fall under your benefit and which are always cash.
Patient Journey
- Referral and booking. The program’s physicians are listed as accepting patient or physician referrals; some also offer telehealth visits and others do not, which you settle when you book. A patient coordinator schedules the first appointment and tells you which records to send — prior cycle notes, labs, imaging, operative reports.
- Evaluation. Hormone panels including AMH, antral follicle count by transvaginal ultrasound, and semen analysis run on the center’s computer-assisted system. Where a loss history or a uterine factor is in play, the workup extends to genetic testing, hysteroscopic assessment of the cavity and immunologic evaluation.
- Plan. Diagnosis, your reproductive goals and your insurance narrow the options to timed intercourse or IUI, IVF with or without ICSI, a donor gamete or gestational carrier path, preservation, or surgery first. Financial counseling runs in parallel rather than after medications start.
- Stimulation and monitoring. Injectables, then serial ultrasounds and bloodwork at the campus you chose, then a trigger and a transvaginal retrieval under sedation.
- Fertilization, culture and testing. Insemination or ICSI in the on-site laboratory, culture to the blastocyst stage, PGT where you have elected testing, and either a fresh transfer or freezing for a later one.
- Transfer and confirmation. A blood pregnancy test roughly 10 to 14 days after transfer, followed by scans to a confirmed fetal heartbeat. Luteal hormone support typically continues to about six weeks, after which care moves to an obstetric provider.
Local Legal Framework
Connecticut handles assisted reproduction by statute and by contract rather than by a single comprehensive ART law, and several of the answers you need are settled by the documents you sign.
- Egg and sperm donation are legal. Written donor agreements are standard, and the donor relinquishes parental rights in them. Because intended-parentage orders vary by how a family is built, line up independent reproductive-law counsel for each side before a cycle, particularly if your donor or carrier lives in another state.
- Gestational surrogacy is permitted, and Connecticut recognizes enforceable surrogacy agreements. Yale’s program requires patients to secure a carrier through an agency, and the carrier undergoes medical and psychological screening before a transfer.
- Genetic testing on embryos. PGT-A and PGT-M face no Connecticut restriction; consent is the medical standard that applies.
- LGBTQ+ access. Connecticut recognized same-sex marriage and parental rights earlier than most states, and following nationwide marriage recognition the framework is uniform. The program’s LGBTQ+ family-building service covers donor insemination, IVF with donor eggs, gestational carrier cycles, and gamete or tissue freezing for transgender patients. Parentage for a donor-conceived child or a child born to a carrier still has to be established by court order, and that paperwork is separate from your medical care.
- Fertility preservation coverage. Connecticut law requires plans to pay for fertility preservation for cancer patients aged 40 and under. Ask your employer benefits office and the center’s financial counselor in writing, before treatment begins.
- Stored embryos. Connecticut has not fixed the legal status of embryos in storage, so disposition consents signed at the time of creation carry the weight. Divorce, separation or a death is exactly when those documents get tested.
Location
- Address: 200 West Campus Drive, Orange, CT 06477
- Phone: (877) 925-3637
- New Haven: 150 Sargent Drive, 2nd Floor, New Haven, CT 06511 — (203) 785-4708
- Westport: 125A Kings Highway North, Westport, CT 06880 — (203) 341-8899
- Guilford: 5 Durham Road, Guilford, CT 06437 — (877) 925-3637
- Stamford: 29 Hospital Plaza, Suite 400, Stamford, CT 06902 — (877) 925-3637










